

A man's leg and knee suffering from bulging veins, obviously affected by venous stasis.

Venous Stasis and Where the Blood Goes After Treatment

Venous stasis breaks the mental model most people bring into the exam room, since they picture a blocked drain line.

That model works for a single fixed channel moving fluid in one direction under pump pressure, but your leg doesn’t work that way at all. Your heart pushes several liters of blood a minute down through the arteries.

That blood has to climb back up against gravity through dozens of parallel routes and thousands of small collateral channels.

Why a Sealed Vein Isn’t a Sealed Pipe

Two structurally distinct networks run side by side to handle that job – the superficial and the deep systems.

By the time a specialist flags a vein for ablation, it has already stopped moving blood forward and instead carries blood backward instead of up toward the heart. Sealing it doesn’t cut off a working route. It removes a vessel that has been pushing blood in the wrong direction for years, often without the patient noticing anything beyond cosmetic changes.

Your vascular specialist leans back from the duplex monitor and says something like “we’re going to shut down,” “seal,” or “ablate” a vein in your leg, and names the vessel involved. Any patient hears that word and pictures a stopped pipe rather than a fixed problem. This is what shows up constantly in exam rooms and health forums.

If you close a major vein in the leg, where does the blood go? Won’t sealing the saphenous vein overload the veins that are left? And 10 years from now, will circulation get worse because a vein got destroyed?

None of these are stupid questions, and they come from picturing veins as fixed, one-way conduits, which they aren’t. It also comes from assuming a diseased vein still moves blood the way a healthy one does, when it doesn’t. Radiofrequency ablation (RFA), or endovenous thermal closure, treats venous stasis and chronic venous insufficiency by shutting down a vessel that has been pushing blood backward, not one that’s still doing its job.

Closing an incompetent vein doesn’t take circulation away. It restores the pressure gradient that lets blood flow the way it’s supposed to.

“Radiofrequency ablation closes off varicose veins in about 97 out of 100 people,” according to Kaiser Permanente. “That means it doesn’t work in about 3 out of 100 people. Veins that do not close may be treated again. Choices include another ablation or another type of procedure.”

The Leaky Valve Behind Venous Stasis

Venous stasis starts upstream, with the basic mechanics of getting blood back to the heart.

Arteries have one job, since the heart contracts and shoves high-pressure blood through them. By the time that blood crosses the capillary beds and enters the veins in the feet and calves, it has lost most of its pressure.

Lower-leg venules run in the single digits, which means getting deoxygenated blood back up from there requires two mechanisms working together.

Your calf muscle pump does the heavy lifting, as the gastrocnemius and soleus contract with every step or ankle flex, compressing the veins buried inside the muscle and driving blood upward. One-way bicuspid valves handle the rest: paper-thin flaps, spaced every few inches, open for upward flow and slam shut the instant gravity tries to pull blood back down.

Genetics stretches the vein wall, pregnancy stretches it further, and years standing on concrete floors or decades sitting at a desk weaken the collagen matrix inside the wall over time.

Once the wall dilates, the valve leaflets can’t meet in the middle, and the seal fails. Stand up and gravity wins, so blood that should climb continuously upward stalls, reverses, and drops back down. Vascular medicine calls this retrograde venous reflux, and the pooling that follows constitutes venous stasis.

Surprisingly, once a saphenous vein develops severe reflux, it stops carrying fresh blood toward the core altogether. Blood climbs through the healthy deep veins, spills sideways into the broken saphenous system through damaged junctions, cascades back down the leg, and pools in the calves, ankles, and feet, then repeats the same circuit.

Your vein has stopped functioning as a route and instead leaks continuously backward, which produces chronic venous hypertension.

The Deep System Does the Work

Your leg runs on two separate venous networks. The superficial system sits just under the skin, above the muscle, and includes the Great Saphenous Vein, the Small Saphenous Vein, and the smaller tributaries, reticular veins, and spider veins visible to the eye.

Even in a healthy leg, this network carries only 5 to 10 percent of total venous return.

The deep system runs beneath a tough layer of muscular fascia, wrapped in thick skeletal muscle, and includes the anterior tibial, posterior tibial, peroneal, popliteal, and femoral veins. It carries more than 90 percent of the blood heading back to the heart. Thick muscular walls, high capacity, and direct contact with the compressive force of the calf and thigh muscles equip it structurally for that load.

Dozens of small perforator veins connect the two systems, with each carrying its own one-way valve that lets blood pass in exactly one direction, never the reverse.

RFA stays entirely within the superficial system, so the treatment never touches the deep veins, which have carried the majority of the body’s blood volume all along. If a surgeon seals the saphenous vein, the blood that used to pool inside it reroutes through healthy perforators into the deep system, which already handles more than nine times that volume without strain.

Reversing Venous Stasis: Swelling, Fatigue, and Skin

Venous stasis leaves marks well beyond the vein itself, and reversing it changes how the lower leg feels within weeks, not just how the ultrasound looks.

Capillary beds that chronic pressure has stretched thin regain their grip on fluid instead of leaking it into surrounding tissue. Less fluid escapes into the fat and muscle.

The swelling that builds by the end of the day, pitting edema and the sock marks it presses into the skin, starts to fade as a result.

The heaviness patients describe in their legs by evening fades too, and it was never muscle fatigue to begin with. Hundreds of milliliters of stagnant blood had been sitting in the calf and ankle for hours, parked in place instead of moving through the system. Once that blood moves efficiently through the deep system, the calf pump works against far less resistance than before.

Skin condition improves as well, since the overloaded capillaries stop leaking red blood cells into the dermis. The itching, flaking, eczema-like patches of stasis dermatitis calm down. The lifetime risk of a venous ulcer near the ankle bone drops substantially, and restless legs and nighttime calf cramping tend to ease up too.

Stagnant venous blood carries a heavy load of lactic acid and metabolic waste that irritates nerve endings in the calf during sleep. Clearing the congestion lets the tissue stay properly oxygenated through the night instead.

“Before undergoing vein ablation, you should talk with your doctor,” states UMass Memorial Health. “While it is safe and effective, it may not be appropriate for everyone. Side effects may include bleeding, pain, swelling, allergic reactions, blood clots (rare), and possible return of your vein condition. It’s important to follow posttreatment instructions. Knowing the risks and side effects ahead of time can help with a good outcome.”

Reading Your Own Ultrasound

Understanding the mechanics changes what a patient can ask a vascular specialist, replacing passive nodding with sharper, more specific questions.

Ask to see the reflux times on the report and severe cases show two, three, even four full seconds of backward flow on the Doppler tracing. That number turns a vague worry into a measurable fact that a patient can actually point to.

Confirm that the deep venous system remains fully patent as well, because a thorough venous ultrasound doesn’t stop at flagging the diseased superficial veins.

It also verifies that the femoral and popliteal veins are open, carry no old clots, and move blood without obstruction. Once the scan shows that deep pathway clear, the patient has a documented answer to where the blood goes after closure.

Ask exactly where the catheter enters, where treatment stops, and which tributaries lose their pressure load once the trunk vein is sealed. Knowing the specific vessels involved turns an intimidating procedure into a mapped-out mechanical fix rather than an abstract threat.

Diseased State (Pre-Ablation Reflux) Treated State (Post-RFA Closure) Clinical Benefit to Patient
Primary Direction of Flow Retrograde (downward toward ankle upon standing) Antegrade only (unidirectional upward return via deep system) Immediate elimination of hydrostatic blood pooling
Venous Reflux Duration Pathological Non-existent; vessel lumen permanently sealed Halts continuous reflux cycle and circulatory recirculation
Ambulatory Ankle Pressure Sustained high (70-90 mmHG during movement) Normalized after muscle pump activation) Removes pressure strain on cutaneous capillaries
Microvascular Permeability High (plasma and red cells leak into interstitial tissue) Normalized (capillary endothelial barrier stabilizes) Rapid reduction in pitting edema and sock indentations
Tissue Oxygenation & Clearance Depressed (stagnant blood stalls metabolic waste removal) Optimized (fresh arterial blood circulates without backlog) Alleviates nocturnal leg cramps, burning, and aching fatigue
Tributary & Branch Vein Strain Severe outward mechanical tension (varicosities expand) Decompressed (secondary branch veins experience no back-pressure) Flattening of varicose clusters; prevents future blowouts
Vessel Structural Status Dilated, diseased collagen matrix with non-coapting valves Fibrotic strand gradually broken down by cellular macrophages Permanent anatomical resolution; zero risk of reflux recurrence in treated segment

Common Questions and Answers

  • Can sealing a superficial vein cause a blood clot in the deep veins? RFA carries a real but low DVT risk. Reported rates vary by study and by how closely researchers look for clots, ranging from well under 1 percent up to around 3 percent within 30 days in larger database reviews. Most single-center series clustering below 1 to 2 percent. Walking right after the procedure activates your calf pump.
  • What about a future coronary bypass? Surgeons harvesting a vein for bypass need one that’s straight, structurally sound, and fitted with competent valves. A saphenous vein that has already dilated and developed severe reflux disqualifies itself from that use. Grafting a failed, valve-incompetent vein into an arterial position tends to fail early anyway, which is part of why cardiac surgery today leans on the internal mammary artery, the radial artery, or synthetic grafts.
  • How fast does blood reroute once the catheter comes out? Essentially instantly. The moment the vessel wall collapses, the downward retrograde flow simply stops.
  • Will the vein grow back or reopen? Once full thermal ablation denatures the endothelial lining and collagen fibers, the process becomes irreversible, and the body clears the vessel permanently.

Closing this vein will not put extra strain on the heart, contrary to what many patients assume. The opposite is closer to the truth, since a refluxing vein forces the heart and vascular system to keep pumping the same blood volume through a pointless local loop. Shutting that loop down streamlines venous return to the right atrium instead.

Compression stockings aren’t a life sentence either, since doctors typically prescribe them for one to two weeks after the procedure. This is mainly for pressing the vein walls together while the seal sets, supporting the deep veins during the initial fluid shift.

Once a follow-up ultrasound confirms closure and healthy deep flow, most people can make daily compression optional – useful mainly for long flights or long stretches on their feet.

“The outcomes showed similar early postoperative occlusion success among all three CVI (Chronic Venous Insufficiency) treatment techniques,” states the Journal of Vascular Surgery and Society for Vascular Surgery. “However, RFA (Radiofrequency Ablation) resulted in a significantly higher success rate compared with EVLA (Endovenous Laser Ablation) at 3 and 5 years of follow-up.”

Wellness and Pain

Discover the right treatment for your venous stasis by visiting Wellness and Pain. We offer conservative treatments, routine visits, and minimally invasive quick-recovery procedures. We can keep you free of problems by providing lifestyle education and home care advice.

This enables you to avoid and manage issues, quickly relieving your inhibiting lifestyle conditions when complications arise. We personalize patient care plans based on each patient’s condition and unique circumstances. Wellness and Pain can help improve wellness, increase mobility, relieve pain, and enhance your mental space and overall health.
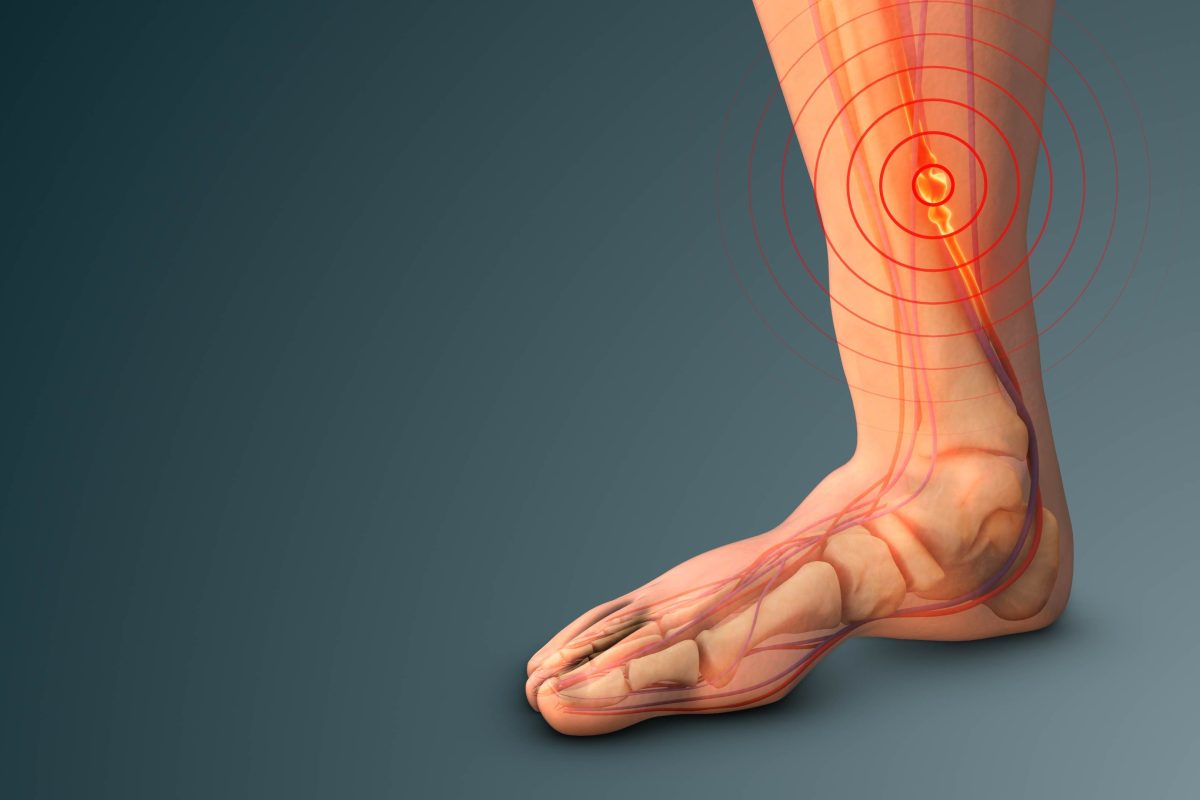
This medical graphical diagram of veins and nerves in a human's leg and foot is illustrative of the concept of vein ablation for diabetic leg pain.

The Solution to Numbness: Vein Ablation for Diabetic Leg Pain

While that sting in your feet or legs means something serious, it also means vein ablation for diabetic leg pain is probably on your radar. High blood sugar can hurt nerves and blood vessels, leading to diabetic neuropathy or slowed blood flow.

Brushing off that pain or numbness can put your mobility at risk, and ignoring these symptoms certainly won’t help you get better.

While there’s no magic fix for this problem, treatments have come a long way. Simple changes in daily habits can make a difference, and new therapies might also help you feel better. The main goal stays clear: ease pain, protect nerves, and keep your legs healthy. Taking immediate action helps patients.

“If you have diabetic neuropathy, then the symptoms will be different and may include weakness in muscles of the foot and leg, an unsteady walk, loss of balance control, poor coordination when walking or running, and stiffness of the legs,” states MantraCare. “It is a diabetic complication that can lead to diabetic foot pain. This type of neuropathy occurs when the small nerves in your feet and legs are damaged by elevated glucose levels over time. Consequently, you may lose feeling or have poor sensation along with an inability to properly control leg movements.”

Nerves, Blood Flow, and Vein Ablation for Diabetic Leg Pain

Before getting into vein ablation for diabetic leg pain, let’s discuss diabetic leg and foot pain. It has two main causes: nerve damage and poor blood flow.

Your nerves are like thin wires running through your body, and too much sugar in your blood works like acid, eating away the insulation and starting to break down the wire inside. A 1978 research study changed how doctors understand this damage. High blood sugar causes these nerves to swell, and when they swell, they lose their strength.

Even a little pressure can hurt them further, making problems like Charcot’s foot likely. This causes bones to get weak and joints to even collapse.

High sugar levels do a number on your blood vessels, too. Your vessels get hard and narrow, so less blood reaches your legs and feet. Healing slows down significantly since vital oxygen and nutrients can’t get through, meaning a tiny scratch could turn into a big sore that refuses to heal.

The danger of infection shoots up, and gangrene becomes possible even from a small wound.

Symptoms show up in several ways. You might feel tingling or numbness, as if your foot has gone to sleep. Some people find even the touch of a soft sock becomes irritating, and ordinary pressure or mild sensations may become much more painful than usual.

Weakness and burning pain might appear without warning. For many, these symptoms get worse with time unless sugar levels get under better control.

“What does this mean clinically? First, we know that if the nerve is edematous, it is more likely to become entrapped in small, non-expandible anatomical tunnels or constrictive areas,” according to MedCentral. “This has been demonstrated in both the upper extremity and in the leg and foot. In fact, the incidence of carpal tunnel syndrome in the general population in the United States is 2%, while in the diabetic population it is estimated to be between 14% and 30%.”

Diagnosis to Action: Foundational Treatments and Testing

Before you get an expert opinion on vein ablation for diabetic leg pain, you need to see where it starts and how severe it is. For this reason, a specialist might order two immediate tests: Electromyography (EMG) and a Nerve Conduction Velocity (NCV) test.

EMG looks at how your muscles react when nerves fire, and this process spotlights possible muscle damage; conversely, NCV checks the speed of signals moving along your nerves.  With these two tests, your doctor finds out if the trouble hits the nerve fibers or the myelin sheath, so treatments can target the source rather than just covering up the pain. This level of detail means the doctor can choose the best way to help, starting right at your feet or legs.

Orthopedic treatments usually focus first on measures like a period of rest or physical therapy. Physical therapy matters a lot because it helps you keep your muscles strong and joints loose, and stretching moves combined with simple strength exercises really do make a big difference.

What’s known as “foundational care” includes:

  • Physical therapy (PT) and rest. This improves range of motion, flexibility, and muscle strength.
  • Medication. The use of NSAIDs (nonsteroidal anti-inflammatory drugs) or muscle relaxants to manage acute pain and inflammation can help.
  • Lifestyle choices. This focuses on an anti-inflammatory diet, the key to supporting blood sugar control and healing.
  • Surgery. As a last resort, this is usually reserved for severe cases like Charcot’s foot or non-healing ulcers requiring debridement.

Surgery usually comes only after everything else has failed. Doctors save it for tough cases that just won’t heal, and sometimes the removal of dead tissue becomes necessary. Most people won’t need surgery unless their condition gets really serious.

What is Vein Ablation for Diabetic Leg Pain?

Vein ablation for diabetic leg pain is a minimally invasive procedure used to treat chronic venous insufficiency (CVI) or varicose veins. CVI is often overlooked, causing leg pain in people with diabetes.

While leg pain in diabetic patients is most often linked to diabetic peripheral neuropathy, poor circulation and vein issues are also common due to diabetes damaging blood vessels. In CVI, the valves in leg veins that push blood back toward the heart become damaged or weakened, causing blood to pool.

This pooling, or reflux, leads to increased pressure, which can manifest as pain, heaviness, swelling, and cramping in the legs, sometimes referred to as venous leg pain. When it comes to a diabetic’s leg discomfort, a vein specialist may recommend an ablation procedure if an ultrasound reveals this underlying venous issue. Correcting the vein problem can alleviate the associated pain and symptoms, even if neuropathy is also present.

The ablation procedure is typically an outpatient, image-guided treatment that uses heat to close off the problematic vein. The two main types are Radiofrequency Ablation (RFA) and Endovenous Laser Ablation (EVLA).

The specialist uses ultrasound guidance to insert a thin tube, called a catheter, into the affected vein. Once positioned, the catheter delivers either radiofrequency waves or laser energy, which generates heat that permanently seals the vein shut.

The body then naturally absorbs the closed-off vein over time. By sealing the malfunctioning vein, the procedure forces the blood flow to reroute immediately to nearby healthy veins, improving circulation and reducing the uncomfortable pressure and pooling that caused the venous leg pain.

This provides relief for the CVI-related symptoms, usually with a quick recovery time compared to traditional vein stripping surgery.

Various Intensive and Supporting Therapies

Basic care works for some and vein ablation for diabetic leg pain works for others, but tough pain calls for unique help. Trigger point injections tackle sore knots in muscles.

For this treatment, a pain doctor uses a small needle to numb the spot, sometimes injecting a steroid as well. The area might hurt a bit more right after, especially if the needle hits the sorest spot. If heat or pain pills don’t help, this kind of targeted injection can break that stubborn pain pattern.

Acupuncture takes a different route, utilizing thin needles inserted into the skin at certain points, which prompts the body to flood the system with feel-good chemicals. These endorphins kick in, easing pain. Some people leave with more energy, while others just feel calm. Many notice lasting relief from symptoms that haven’t budged with other treatments.

Specialized treatments include:

  • Trigger point injections. These target specific muscle knots with anesthetics and corticosteroids to reduce localized pain.
  • Acupuncture therapy. This stimulates the body to release natural painkillers and neurotransmitters, relieving chronic symptoms.
  • Therapeutic massage. It boosts blood flow and tissue healing, reduces inflammation, and lowers stress hormones.
  • IV hydration. This delivers fluids, electrolytes, and nutrients like Magnesium and B vitamins directly to the bloodstream for faster recovery and electrolyte balance.

Therapeutic massage can offer more than just relaxation. It helps muscles heal, lifts your mood, and improves blood flow to the arms and legs. People with diabetes or foot pain often feel significant relief after a session. Some massage methods push out built-up fluid and bring down swelling, while the simultaneous drop in cortisol levels may ease stress.

IV hydration works differently because nutrients go straight into the bloodstream through a needle. The fluids carry key minerals like magnesium, potassium, and B vitamins, which helps energy return faster, replaces lost minerals, and speeds up recovery. Since chronic illnesses can drain the body, a quick nutrient boost can make a real difference in vitality.

Breakthrough: A New Hope for ‘No-Option’ Ulcers

Patients living with diabetic foot ulcers (DFU) and tough artery problems run out of options fast, as traditional treatments like bypass surgery or angioplasty just aren’t possible for some. For these cases, something new is showing promise.

A recent study looked at adding bipolar radiofrequency ablation to a Lumbar Sympathetic Block. The main idea is to block the nerve signals that keep blood vessels tight. Once those signals stop, blood flow improves in the leg, allowing wounds to heal more effectively.

The numbers from the study are surprising, revealing that over half of the patients getting this new treatment saw their wounds close up, while only a handful in the old treatment group healed. Thankfully, none of the people who tried this new method lost a leg.

“DFUs, frequently associated with peripheral arterial disease (PAD), represent a significant complication of diabetes mellitus,” states part of the findings published in Sage Journals. “In patients unsuitable for surgical revascularization, these treatment-resistant wounds, often accompanied by infection and tissue loss, not only increase the risk of amputation and severely impair quality of life, but also significantly elevate the risk of mortality. This necessitates the exploration of alternative therapeutic strategies.”

Pain was also much lower, with patients reporting that both nerve pain and their general pain had dropped by the six-month checkup. Additionally, the treatment turned out to be safe with very few issues reported.

For anyone facing the threat of amputation with no other solutions, this breakthrough matters greatly, providing a necessary way forward when everything else has failed.

Prevention and Protection vs. Vein Ablation for Diabetic Leg Pain

Daily routines make the biggest difference in managing whether or not you’ll need vein ablation for diabetic leg pain. No treatment will help if you skip the basics.

Since neuropathy often sneaks up, even small scrapes can go unnoticed; therefore, you must look at your feet every single day, checking for cuts, any redness, or warts. Don’t skip the bottoms of your feet or those tricky spaces between your toes.

Keep your feet clean with warm water and soap, but skip long soaks to avoid drying your skin. Dry every spot well, and then sprinkle powder between your toes to block moisture accumulation.

Choose shoes that fit well, pick socks with smooth seams, or wear supportive slippers indoors. Never go barefoot, not even for a minute. Your feet need warmth in winter and shade in summer, so remember to rest with your feet raised every so often. To maintain good circulation, wiggle your toes and circle your ankles, but keep your socks loose to help blood flow.

Sometimes trouble creeps in fast, so watch for any cut, blister, or sore that won’t heal after a day. You should call the doctor immediately if you see warmth, swelling, or red spots. Also, that dried blood in a callus can mean something deeper, and black spots with a bad smell are an emergency.

Keep regular appointments with your doctor to stay ahead of problems, and watch your blood sugar closely. These essential habits will help you keep moving and feeling your best.

Care Action Rationale
Daily Inspection Check both feet every day for cuts, blisters, sores, swelling, or skin color changes. Use a mirror or ask a family member for help. Early detection is vital, especially with nerve damage masking pain.
Hygiene Wash feet daily with mild soap and lukewarm water. Dry them thoroughly, especially between the toes. Prevents fungal infections like athlete’s foot and bacterial growth.
Moisture Apply lotion to the tops and bottoms of your feet, but avoid applying lotion between the toes. Prevents dry, cracked skin, which can lead to entry points for bacteria. Keeping lotion out of the toes prevents excessive moisture buildup.
Footwear Never walk barefoot. Always wear socks and properly fitting, protective shoes. A podiatrist may recommend special diabetic footwear to prevent pressure points. Protects feet from injury and friction that can cause blisters or sores.
Nail Care Trim toenails straight across and file the edges gently. Prevents ingrown toenails, which can easily become infected.
Circulation Put your feet up when sitting and wiggle your toes frequently to keep blood flowing. Promotes optimum blood circulation to the lower limbs.
Lifestyle Manage blood sugar levels and do not smoke. High blood sugar and smoking deplete blood flow, aggressively worsening diabetic foot issues.
Professional Care See a doctor or podiatrist for regular foot checkups, and never try to treat corns, calluses, or ingrown toenails yourself. Professional care ensures early diagnosis and safe treatment of minor issues.

Frequently Asked Questions (FAQ)

Here are answers to the most common questions regarding managing diabetic leg and foot pain, as well as its relationship to finding the best vein ablation for diabetic leg pain:

  • Q: Can diabetic nerve pain be cured?
  • A: Currently, there is no single cure for diabetic neuropathy, but the condition can be effectively managed. The primary goal of treatment is to relieve the pain and prevent further nerve damage by rigorously controlling blood sugar levels. Early intervention using medications, physical therapy, and lifestyle modifications offers the best chance of successful long-term management.
  • Q: What is the main difference between an EMG and an NCV test?
  • A: Both tests diagnose nerve issues, but they measure different things. The Electromyography (EMG) measures the electrical activity of your muscles in response to nerve stimulation. The Nerve Conduction Velocity (NCV) Test measures the actual speed and strength of electrical signals traveling through your peripheral nerves. The NCV test is key for determining if the damage affects the nerve fibers or the protective myelin sheath.
  • Q: Why is circulation so important for diabetic foot health?
  • A: Poor circulation is a major contributor to diabetic foot complications. When blood flow is restricted due to vessel damage, oxygen and immune cells cannot reach the feet efficiently. This means that minor injuries and ulcers take a long time to heal and can easily become infected, which can lead to severe conditions like gangrene or amputation if not managed immediately.
  • Q: How do Trigger Point Injections help with diabetic leg pain?
  • A: Trigger point injections are used to treat painful, localized knots (active trigger points) in muscle tissue that often contribute to chronic pain, even when the underlying nerve damage is present. The injection, which usually contains a local anesthetic and a corticosteroid, directly numbs the area and reduces inflammation, providing targeted relief when systemic or oral medications haven’t been effective.
  • Q: Is it safe to use massage therapy if I have severe neuropathy?
  • A: Yes, therapeutic massage is generally safe and often highly effective when performed by a professional aware of your condition. Massage is beneficial because it helps increase blood flow to the extremities, reduces inflammation, and lowers stress hormones like cortisol, all of which support overall tissue healing and pain reduction.
  • Q: What does it mean if I find dried blood inside a callus?
  • A: This is an urgent red flag. Calluses with dried blood inside are often the first visible sign of an underlying wound or ulcer that has gone unnoticed due to numbness (neuropathy). This means the wound is already deep enough to bleed and requires immediate medical attention to prevent severe infection and potential progression to gangrene.

Wellness and Pain

Find your personalized vein ablation for diabetic leg pain by visiting Wellness and Pain. We offer conservative treatments, routine visits, and minimally invasive quick-recovery procedures. We can keep you free of problems by providing lifestyle education and home care advice.

This enables you to avoid and manage issues, quickly relieving your inhibiting lifestyle conditions when complications arise. We personalize patient care plans based on each patient’s condition and unique circumstances. Wellness and Pain can help improve wellness, increase mobility, relieve pain, and enhance your mental space and overall health.
Elderly woman in white panties shows cellulite and varicose veins on a light isolated background, in need of a vein clinic.

What to Expect From a Vein Clinic: Treatments, Costs, and Results

Did you notice your veins becoming more visible, your legs feeling heavier, or swelling that won’t go away? These symptoms are more common than many people realize, and they often point to underlying vein issues.

A vein clinic can help. But what exactly do they treat? When should you go? And what kinds of treatments are available?

This guide answers those questions and more. You’ll learn about how to choose the best vein clinic to treat your varicose and spider veins.

What Is a Vein Clinic?

A vein clinic is a medical facility that focuses on diagnosing and treating problems with your veins. These clinics help people manage cosmetic concerns, like spider veins, and medical issues that affect blood flow.

You don’t need a referral or a serious diagnosis to make an appointment. If you’ve noticed changes in your legs or are concerned about your vein health, it’s worth getting checked.

Vein clinics handle a range of conditions that affect circulation, especially in the legs. These may include:

  • Spider veins: Thin, visible veins just under the skin, often red or blue
  • Varicose veins: Larger, twisted veins that may bulge or feel tender
  • Chronic venous insufficiency: When blood doesn’t flow properly and pools in the legs
  • Leg swelling, heaviness, or discomfort: Often signs of poor circulation

Many of these issues develop slowly over time. Even if symptoms seem minor now, early treatment can prevent more serious complications later.

Who Is a Good Candidate for Vein Care?

Anyone experiencing symptoms like leg pain, swelling, visible veins, or fatigue that worsens by the end of the day should consider visiting a vein clinic. Some people seek care for appearance-related concerns, while others are focused on comfort or long-term health.

You may also be at higher risk for vein problems if you:

  • Sit or stand for long periods at work
  • Have a family history of vein conditions
  • Are pregnant or have recently given birth
  • Are over age 40
  • Have circulatory issues or are overweight

If any of this sounds familiar, know that there’s nothing to worry about. There are effective and low-risk treatments available.

Who Will You See at a Vein Clinic?

Most vein clinics are staffed by physicians who specialize in vein health. This may include:

  • Phlebologists: Doctors trained specifically in vein conditions.
  • Vascular surgeons: Specialists who can perform more advanced procedures if needed.
  • Interventional radiologists: Doctors who use medical imaging to perform precise, image-guided procedures without traditional surgery.

These providers are experienced in diagnosing the root cause of your symptoms and guiding you through your options with care and clarity.

Conditions Commonly Treated at a Vein Clinic

Vein clinics diagnose and treat a wide range of vein conditions, many of which cause more than just visible veins. They can lead to discomfort, fatigue, and more serious medical issues if left untreated.

Understanding what’s being treated can help you recognize when it’s time to seek professional care.

Varicose Veins

Varicose veins are large, twisted veins that often appear on the legs. They may look blue or purple and can feel heavy, itchy, or sore by the end of the day. These veins are caused by damaged veins where the one-way valves stop working properly, allowing blood to pool instead of flowing back toward the heart.

If left untreated, varicose vein disease can worsen and lead to other venous disorders, such as skin discoloration or open sores.

Spider Veins

Spider veins are smaller, web-like clusters of red or blue veins that typically appear just beneath the surface of the skin. While they don’t usually cause physical pain, they’re a common reason people seek spider vein treatments for cosmetic reasons.

Ultrasound-guided sclerotherapy is a common technique used to treat both spider and small varicose veins, where a solution is injected to close off the affected area.

Chronic Venous Insufficiency

In chronic venous insufficiency, the veins in your legs can’t send blood back to your heart. This leads to swelling, skin discoloration, and sometimes leg ulcers. It’s a progressive venous disease that can worsen over time if not addressed.

Early diagnosis and consistent treatment at a certified medical center can prevent further damage.

Deep Vein Thrombosis

Deep Vein Thrombosis (DVT) involves a blood clot forming in a deep vein, often in the thigh or calf. This condition is more serious and may cause redness, warmth, or sharp pain. While most vein clinics focus on outpatient care, they also help recognize signs of blood clots and will refer patients to urgent care if needed.

Types of Treatments Available at a Vein Clinic

If you’re exploring options for treating vein issues, you’re likely looking for something that works without disrupting your life. Most modern vein treatments are gentle, effective, and performed in-office with little to no downtime.

Below are the most common procedures offered at vein clinics. Understanding each one can help you feel more prepared to discuss what’s right for your needs.

Non-Surgical and Minimally Invasive Options

Many patients start with non-surgical care. These treatments are widely used, typically covered by most insurances, and designed to restore comfort and circulation.

  • Compression therapy: Wearing special socks that help improve blood flow and reduce swelling.
  • Sclerotherapy: Your provider injects a special solution into small veins, which causes them to collapse and gradually disappear.
  • Endovenous ablation: A thin fiber or catheter uses heat to close off bulging veins from the inside.

Procedures like radiofrequency ablation use radiofrequency energy to gently seal the vein. This type of minimally invasive procedure is especially effective for larger varicose vein treatments and is done using only local anesthesia.

Advanced Techniques and Newer Approaches

Some clinics offer innovative options that can improve comfort and healing time. These include:

  • VenaSeal: A medical adhesive that closes veins without heat or tumescent anesthesia
  • Varithena: A microfoam injected to treat larger, twisted veins with fewer needle sticks
  • Ultrasound guidance: Enhances precision by mapping deeper vein conditions before treatment

These advanced therapies often provide fast relief, especially for venous insufficiency, and are ideal for those seeking targeted care with minimal disruption.

Surgical Options for Severe Cases

When vein issues are advanced or not responding to non-surgical methods, minor outpatient surgery may be recommended.

  • Ambulatory phlebectomy: Tiny incisions are made to remove twisted veins close to the skin
  • Vein ligation and stripping: Rarely used today, but still available for complex cases under specialist care

These options are handled by board-certified vascular surgeons who specialize in vascular surgery and venous medicine. They’ll carefully review your treatment options and discuss whether a surgical plan makes sense for your situation.

What to Expect During Your First Vein Clinic Appointment

Most appointments begin with a consultation and physical exam. Your provider will ask about your symptoms, lifestyle, and any previous health concerns related to vein problems or circulation.

If your doctor suspects a deeper issue, they may order an ultrasound. This painless scan uses sound waves to show how blood is moving through your veins. It’s often used to detect venous insufficiency, damaged veins, or other vein disorders that aren’t visible from the surface.

This step is essential for confirming a diagnosis and ruling out more serious conditions like deep vein thrombosis.

Questions to Ask During Your Visit

To make the most of your appointment, come prepared with a few questions. Consider asking:

  • What type of vein treatments do you recommend for my condition?
  • Will the procedure be done here or referred elsewhere?
  • What is the recovery time?
  • Will insurance help cover the costs?

These conversations help you understand your treatment options and allow your provider to tailor care to your specific needs.

What to Bring With You

Bring your insurance card, a list of current medications, and any previous medical records related to your vein conditions. If you’ve noticed any specific symptoms like leg heaviness, swelling, or changes in skin color, make a note of when they started and how they’ve changed.

The more detail you can provide, the easier it will be for the clinic to create a personalized plan for your care.

Recovery and Results After Vein Treatment

Many people worry about what happens after the procedure. Will it hurt? How long will it take to get back to normal? The good news is that most vein treatments involve minimal recovery and allow you to return to your routine quickly.

Most treatments are done in-office and don’t require a hospital stay. You’ll usually be able to walk out the same day. Your provider might recommend walking daily and wearing compression stockings to support healing.

Discomfort is usually mild and temporary. You may feel some tightness or notice bruising near the affected area, but it typically fades within a few days.

Are Results Permanent?

In many cases, the treated vein closes off and fades, and blood is naturally rerouted to healthier veins. While treatment is effective, new vein problems can develop over time, especially if underlying causes, like prolonged standing or genetics, remain.

Your provider may suggest follow-up visits or lifestyle changes to help prevent recurrence. Staying active, maintaining a healthy weight, and elevating your legs when resting can make a big difference.

When Do Visible Results Appear?

Cosmetic changes, such as fading spider veins or reduced visibility of bulging veins, can take a few weeks to a few months, depending on the treatment. Relief from symptoms like leg heaviness, itching, or swelling often begins within days.

Be patient if you’re treating varicose veins or venous conditions for health and appearance. Gradual improvement is normal, and your provider will monitor your progress during follow-ups.

How Much Does Treatment at a Vein Clinic Cost?

The cost of treatment depends on the type of procedure, how many sessions you need, and whether your insurance helps cover it. Some treatments are considered medically necessary, while others are viewed as cosmetic.

For example, the average cost of spider vein treatments like sclerotherapy is around $500 per session. More advanced treatments, such as radiofrequency ablation or ambulatory phlebectomy, may cost more.

What Affects Treatment Costs?

Costs can vary based on:

  • The size and location of the veins
  • Whether multiple areas are being treated
  • The technology used
  • The experience of the provider

If you’re visiting varicose vein clinics for visible symptoms or discomfort, your care may be covered by insurance.

Does Insurance Help Cover Treatment?

Most insurances, including major providers like Blue Cross, Blue Shield, and United Healthcare, cover treatments that are medically necessary. This usually applies if you’re experiencing pain, swelling, skin ulcers, or other signs of venous disease.

Your clinic can often submit documentation on your behalf to show medical necessity. If you’re not sure what your plan includes, ask the clinic’s staff to help you check your benefits before your appointment.

What to Look for in a Vein Clinic

Choose a provider that’s experienced, well-reviewed, and equipped to treat a full range of vein conditions.

When researching clinics, look for:

  • Board-certified vein doctors or vascular surgeons
  • A variety of treatment options, including both cosmetic and medical care
  • Modern equipment and techniques
  • Positive patient reviews and clear communication

Clinics that specialize in venous and lymphatic medicine are often more prepared to handle complex cases, including chronic venous insufficiency or venous disorders.

You can search online for local providers using platforms like Google Reviews. Many websites list provider credentials, available procedures, and insurances accepted, which can help narrow your options.

Get Trusted Vein Care at Wellness and Pain

If you experience leg discomfort, swelling, or visible veins, Wellness and Pain provides advanced treatment in a supportive, patient-focused setting. Our team treats everything from spider veins to chronic venous insufficiency using modern, minimally invasive procedures.

Wellness and Pain performs treatments like sclerotherapy and radiofrequency ablation in-office with minimal recovery time. Most treatments qualify for coverage through major insurers such as United Healthcare, Blue Cross, and Blue Shield.

Our vein specialists assess your symptoms, confirm a diagnosis, and create a personalized care plan that matches your needs. They address both medical and cosmetic concerns to help you feel better and more confident.

You can schedule an appointment easily and expect a comfortable, guided experience from start to finish.

Book your appointment today!

FAQs About Vein Clinic

How much does it cost to get your veins done?

The cost depends on the treatment and the severity of your vein disease. For example, sclerotherapy for spider veins averages about $500 per session. More advanced procedures may cost more, but could be covered by insurance if they’re medically necessary.

Are vein clinics covered by Medicare?

Medicare and other insurers may cover treatment if it’s needed for medical reasons, such as leg ulcers, venous insufficiency, or chronic venous insufficiency. Cosmetic treatments typically aren’t covered. Always check with your provider and insurance plan before scheduling a procedure.

What is the best drink for varicose veins?

Water is always important, but drinks rich in antioxidants, like citrus juice, beet juice, or green tea, may help support circulation. These won’t cure varicose veins, but they can complement a healthy lifestyle and support vein function.

What happened to Vein Clinics of America?

Vein Clinics of America closed many of its locations in recent years. Some offices transitioned to different management or merged with other vein care providers. If you’re looking for a trusted alternative, Wellness and Pain offers modern vein treatments, including diagnostic imaging and minimally invasive procedures.

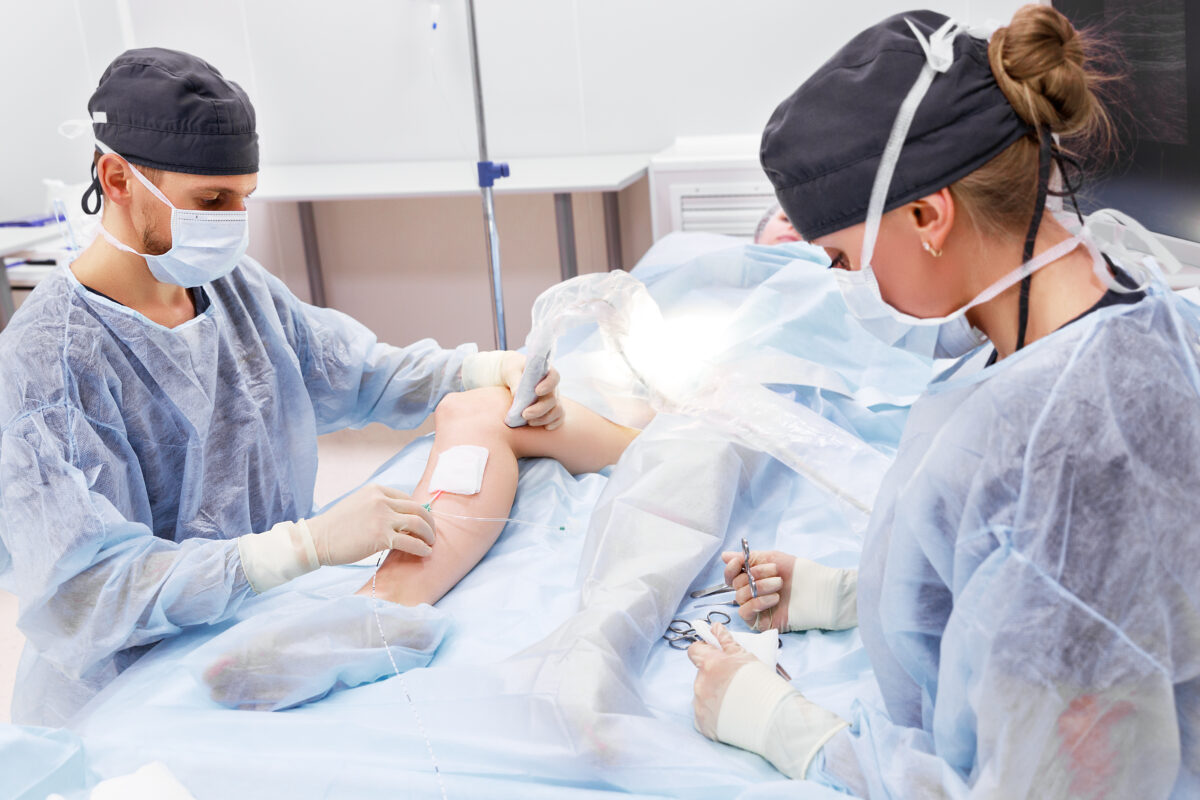
A pain management specialist doctor performs deep vein ablation treatment on a patient during minimally invasive surgery.

Deep Vein Ablation Treatment and Post-Procedure Care

Deep vein ablation is an effective treatment for varicose veins, offering long-term relief with only a 2-5 percent chance of recurrence.

It’s important to note that some studies report a higher overall recurrence rate, around 22 percent, which might seem concerning at first. However, this often reflects the development of new varicose veins in different areas of the leg, rather than a failure of the initial treatment. Even after one pathway is closed, other pathways may develop due to vein wall weakness.

Recurrence often occurs after 3 years, but many remain recurrence-free for 8 to 10 years, proving the treatment’s effectiveness. Several factors can influence the likelihood of varicose veins returning. These include the reopening of the treated vein (recanalization), the development of new varicose veins in other leg veins, and issues with perforator veins (veins connecting superficial veins to deep veins).

To minimize the risk of recurrence, it’s essential to ensure that your initial treatment is comprehensive and addresses all sources of venous insufficiency in the leg.  This means your vein specialist will carefully evaluate your condition and treat all problematic veins, not just the most obvious ones.

To ensure long-term success, follow post-treatment care instructions diligently. This includes wearing compression stockings, elevating your legs, and engaging in regular exercise. Maintaining a healthy lifestyle, like managing weight and staying active, is key and should be consolidated with other related advice in the text to reduce redundancy.

If you’re considering endovenous ablation or have concerns about varicose vein recurrence, it’s always best to consult with a qualified vein specialist. They can assess your individual risk factors, discuss your treatment options, and provide personalized guidance for preventing recurrence and maintaining healthy leg veins

Factors Increasing Varicose Vein Likelihood after Deep Vein Ablation

While deep vein ablation is effective, certain factors can increase recurrence risk, making understanding them crucial for long-term success. Incompetent perforator veins, connecting superficial to deep veins, often lead to new varicose veins even after ablation. Another common cause of recurrence is recanalization, where a previously treated vein reopens. New varicose veins may form in veins like the anterior accessory great saphenous vein (AAGSV) or small saphenous vein (SSV).

It’s crucial to address all sources of venous insufficiency during the initial procedure to minimize the risk of recurrence.  Ablation techniques may affect outcomes, with radiofrequency showing slightly higher recanalization rates than laser. Patient factors like obesity and pelvic vein compression (e.g., May-Thurner syndrome) also raise recurrence risk.

Other factors contributing to recurrence include the formation of new blood vessels (neovascularization) and the persistence of reflux in certain veins.  It’s important to remember that the risk of recurrence generally increases with time after the initial procedure.

“The majority of recurrences were in association with perforating veins,” states The Scientific World Journal in Wiley Online Library. “New AAGSV and SSV insufficiency was responsible for 40 percent of those patients who developed recurrent venous disease. The use of standard protocols and routine US examinations may reduce the frequency of saphenous vein recanalization after thermal ablation.”

Three months after vein treatment, patients should be re-examined for any remaining varicose veins causing symptoms. Further treatment will be determined based on the findings of this evaluation.

“Patients should be educated that varicose veins are a chronic recurrent disease, and routine reevaluation and treatment are warranted,” according to Endovascular Today. “Maintaining a healthy active lifestyle, avoiding obesity, and using compression are important activities of long-term management.”

Perforating Veins and Recurrence After Ablation

Perforating veins, which connect surface to deep veins, are crucial to varicose vein recurrence if they malfunction, even after successful deep vein ablation.

Here’s what you need to know about perforating veins and varicose vein recurrence: 

  • They are a major source of recurrence. Studies show that perforator vein issues are present in a significant number of patients with recurrent varicose veins.
  • They contribute to recurrence in multiple ways. They can act as a source of reflux, leading to new varicose veins. They can contribute to the reopening of previously treated veins. They can feed blood into recanalized veins, further promoting recurrence.
  • Their location matters. Perforating veins in the thigh are more likely to cause problems than those in the calf.
  • They often go untreated. Many ablation procedures don’t address perforating veins, potentially leaving a source for recurrence.

How can treating perforating veins help? 

  • Reduce Reflux: By closing off incompetent perforators, you eliminate a major source of backward blood flow that leads to new varicose veins.
  • Prevent Recanalization: Treating perforators can help prevent treated veins from reopening.
  • Improve Overall Vein Function: Addressing perforator issues can improve blood flow in your legs and reduce the risk of complications like ulcers.

Treatment options for perforating veins: 

  • Ultrasound-Guided Sclerotherapy: This is often the first-line treatment, involving injecting a solution into the vein to close it off.
  • Endovascular Thermal Ablation: This uses laser or radiofrequency energy to close the vein and is an option for those who don’t respond to sclerotherapy.

While perforating veins are a key factor in varicose vein recurrence, it’s important to remember that other factors are also involved.  A comprehensive approach that addresses all potential sources of recurrence is essential for long-term success.

Ensuring the Best Possible Outcome after Deep Vein Ablation

To get the best results from your deep vein ablation and reduce the chance of them coming back, it’s important to make informed decisions and follow your doctor’s recommendations. Here’s what you should know:

  • Endovenous ablation techniques, like radiofrequency ablation (RFA) and endovenous laser ablation (EVLA), are very effective. Both have high success rates and low recurrence rates (around 2-5 percent).
  • RFA: Uses radiofrequency energy to heat and close the vein. It’s generally known for being more comfortable with fewer side effects.
  • EVLA: Uses laser energy to close the vein. Advancements in laser technology are making this option increasingly comfortable.

 The best choice for you will depend on your individual needs and the specifics of your condition. Your doctor will consider factors like the size and location of your varicose veins, your overall health, and their own experience with each technique.

Both RFA and EVLA are minimally invasive procedures performed under local anesthesia. They typically take less than an hour, and you can usually go home the same day. You might need to wear compression stockings for a while afterward, but some newer techniques may not require this.

Both procedures have a quick recovery time, allowing you to return to normal activities within a day or two. Complications are rare, but it’s important to be aware of the possibility of endovenous heat-induced thrombosis (EHIT), a type of blood clot.

Solutions: Compression, Lifestyle, and Weight

Taking care of your veins after deep vein ablation involves wearing compression stockings, maintaining a healthy lifestyle, and managing your weight. Compression stockings improve blood flow by supporting veins and reducing swelling. Proper sizing and consistent use maximize their benefits.

“Compression socks have different compression strengths, measured in millimeters of mercury, or mmHg,” states Very Well Health. “There’s a considerable range from nonmedical grade socks, which provide mild (8–15 mmHg) or moderate (15–20 mmHg) compression, to medical grade compression socks of 20–30 mmHg and 30–40 mmHg. Apple says a 20–30 mmHg compression level should be adequate for varicose vein relief or after spider vein treatment.”

A healthy lifestyle is vital for vein health. Regular exercise improves circulation and strengthens leg muscles. Elevating legs, staying hydrated, and eating a low-sodium diet also help. Weight management prevents vein issues by reducing pressure on veins. Even small weight loss improves circulation. Combine exercise with a healthy diet and consider consulting a nutritionist.

Treated veins rarely return, but new ones may develop. Follow up regularly with your provider and address new symptoms promptly. Following these steps with a specialist reduces varicose recurrence risk and ensures healthier legs.

You can personalize your treatment by exploring endovenous ablation at Wellness and Pain. We offer conservative treatments, routine visits, and minimally invasive quick-recovery procedures. We can keep you free of problems by providing lifestyle education and home care advice.

This enables you to avoid and manage issues, quickly relieving your inhibiting lifestyle conditions when complications arise. We personalize patient care plans based on each patient’s condition and unique circumstances. Wellness and Pain can help improve wellness, increase mobility, relieve pain, and enhance your mental space and overall health.

Wellness and Pain 

You can personalize your treatment by exploring deep vein ablation at Wellness and Pain. We offer conservative treatments, routine visits, and minimally invasive quick-recovery procedures. We can keep you free of problems by providing lifestyle education and home care advice.

This enables you to avoid and manage issues, quickly relieving your inhibiting lifestyle conditions when complications arise. We personalize patient care plans based on each patient’s condition and unique circumstances. Wellness and Pain can help improve wellness, increase mobility, relieve pain, and enhance your mental space and overall health.

We Accept Most Insurances

Wellness and Pain accepts most major insurance plans. Here is a list of some of the major insurance plans we accept. If you do not see your insurance plan listed, please call our office to confirm.

Call Us Appointment Locations
Hi, How Can We Help You?






